A quiet shift inside the body showed up on routine scans months before pancreatic cancer took center stage.
Story Snapshot
- Computed tomography can measure muscle and two types of body fat, not just weight.
- Studies track steady drops in muscle and fat around the time of pancreatic-cancer diagnosis.
- Muscle loss links to survival, making it more than a cosmetic change.
- Doctors do not use a single cut point yet, but the trend line matters.
What CT Scans Can See That Scales Cannot
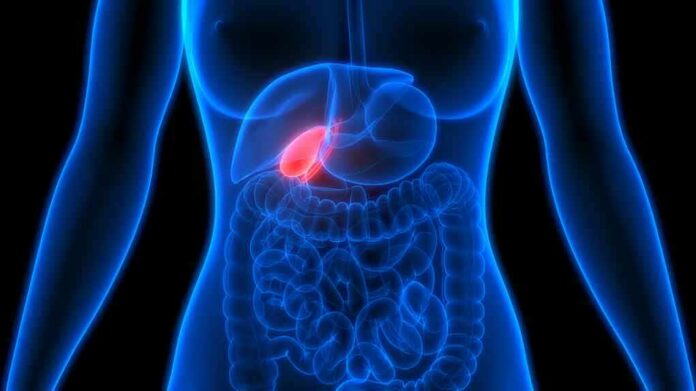
Radiologists can extract hard numbers for muscle, subcutaneous fat under the skin, and deeper visceral fat from a single computed tomography slice through the abdomen. That image, usually taken at the third lumbar vertebra, turns a vague “weight change” into a precise map of tissue. Reviews show standard body mass index can mask muscle loss and fat shifts, while computed tomography lays them out in separate bins that doctors can track over time.
Large cohorts now prove this is not a niche trick. One team analyzed more than one thousand six hundred people with pancreatic ductal adenocarcinoma using a validated deep-learning tool on a twenty-centimeter abdominal section. They linked computed tomography measures of muscle and fat to survival, which shows these numbers carry clinical meaning, not just imaging trivia. When software and scanners line up at scale, patterns stop looking like flukes and start looking like signals.
The Body’s Early Red Flag: A Downward Drift
Longitudinal studies report that skeletal muscle, subcutaneous fat, and visceral fat tend to fall between an initial scan and a short follow-up around two months in pancreatic cancer. That drop fits the known biology of cancer-related wasting, which blends inflammation, appetite loss, and changes in how the body uses energy. One analysis found sarcopenia, or low muscle mass, in about two-thirds of patients at baseline, underscoring how common the pattern is by the time cancer is on the table.
These changes are not cosmetic. They alter strength, recovery, and how well patients tolerate treatment. That is why the measured loss matters more than the bathroom scale. The precise mix also matters. Visceral fat sits around organs and links to inflammation. Subcutaneous fat cushions and stores energy. Muscle drives function, independence, and metabolism. Watching all three move together gives a fuller picture than any single number can offer on its own.
Why Muscle Loss Changes Outcomes
Survival analyses connect the dots between tissue change and time. In a randomized cohort, people who lost skeletal-muscle index had a median overall survival near twenty-five months, while those who gained muscle approached fifty-one months. The p value crossed the usual threshold for significance. That gap does not prove cause, but it argues that muscle is not just along for the ride; it marks a steeper or gentler path through the disease.
Other computed tomography studies echo the theme. When researchers used artificial intelligence to quantify body composition at diagnosis, the variables tied to outcomes even after adjusting for standard factors. The finding matches clinical common sense: a body stripped of reserves has less to give when surgery, chemotherapy, or infection hits. These links strengthen the case for pulling muscle and fat data out of every eligible scan and putting it in the chart, not leaving it trapped in pixels.
What This Means For Patients And Doctors Right Now
Unintentional changes in body make-up deserve attention, especially when they come with other warning signs like abdominal pain, back pain, jaundice, new-onset diabetes, or digestive issues. Guidelines push for quick computed tomography when red-flag symptoms cluster in older adults. Adding computed tomography-based body composition to that work-up can sharpen risk sense without another test, since the numbers come from images doctors already order for many reasons.
Clinicians do not yet have a single cut point that says “screen for pancreatic cancer now” based only on muscle or fat loss. Studies so far focus on diagnosis time and early follow-up, prognosis, and treatment course. Still, the pattern is consistent with cancer cachexia biology and common in pancreatic cancer. The practical path today is simple: note the trend, pair it with symptoms, and escalate imaging and specialist input sooner rather than later when the clinical picture fits.
How To Make The Signal Clinically Actionable
Two steps would lock this into practice. First, release and analyze true prediagnostic cohorts with dates, scan intervals, and matched controls to confirm that tissue loss precedes diagnosis at a usable lead time. Second, set and validate rate-of-change thresholds for muscle, subcutaneous fat, and visceral fat that help triage patients. Prospective studies can test whether acting on these cues moves diagnosis earlier and improves survival without a flood of false alarms.
The conservative play is also the common-sense one: measure what we already image, watch the direction of change, and act when that direction fits the rest of the story. Computed tomography turns a hunch about “weight” into a set of numbers that can guide timing and care. In a cancer known for late detection, every honest signal we can read a little sooner is worth pulling into the light.
Sources:
frontiersin.org, mayoclinic.elsevierpure.com, pmc.ncbi.nlm.nih.gov, pubmed.ncbi.nlm.nih.gov, journals.plos.org, link.springer.com, onlinelibrary.wiley.com